
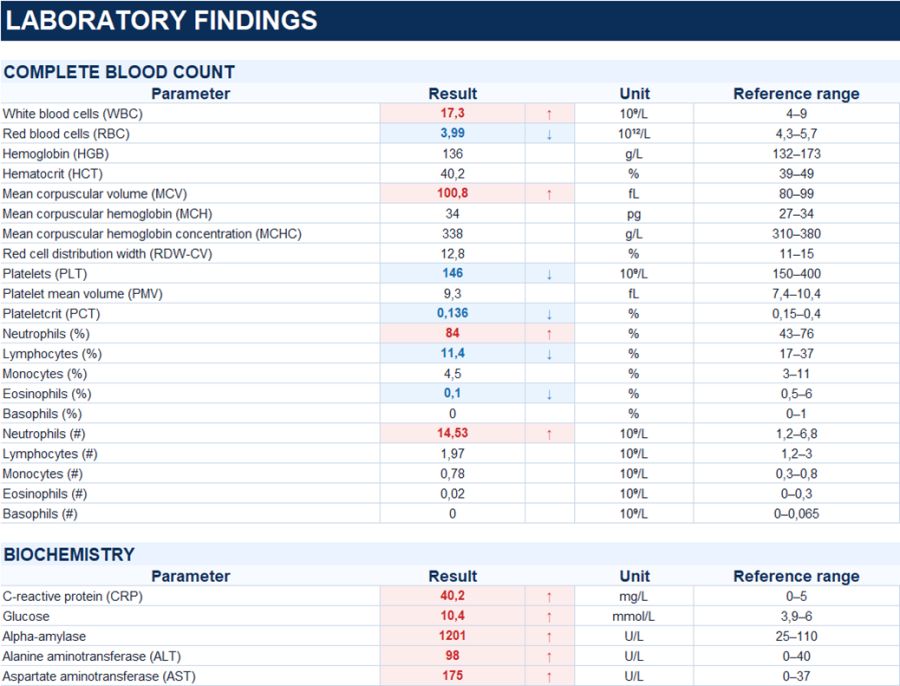
The diagnosis was established based on the characteristic clinical presentation, a more than tenfold elevation of serum α-amylase above the upper reference limit, and corresponding ultrasound findings.
Study method
Ultrasound
Clinical information
A 38-year-old male presented with acute upper abdominal pain accompanied by nausea and vomiting. The symptoms developed after approximately one week of heavy alcohol consumption. On admission, the patient was hemodynamically stable; the smell of alcohol was noted.
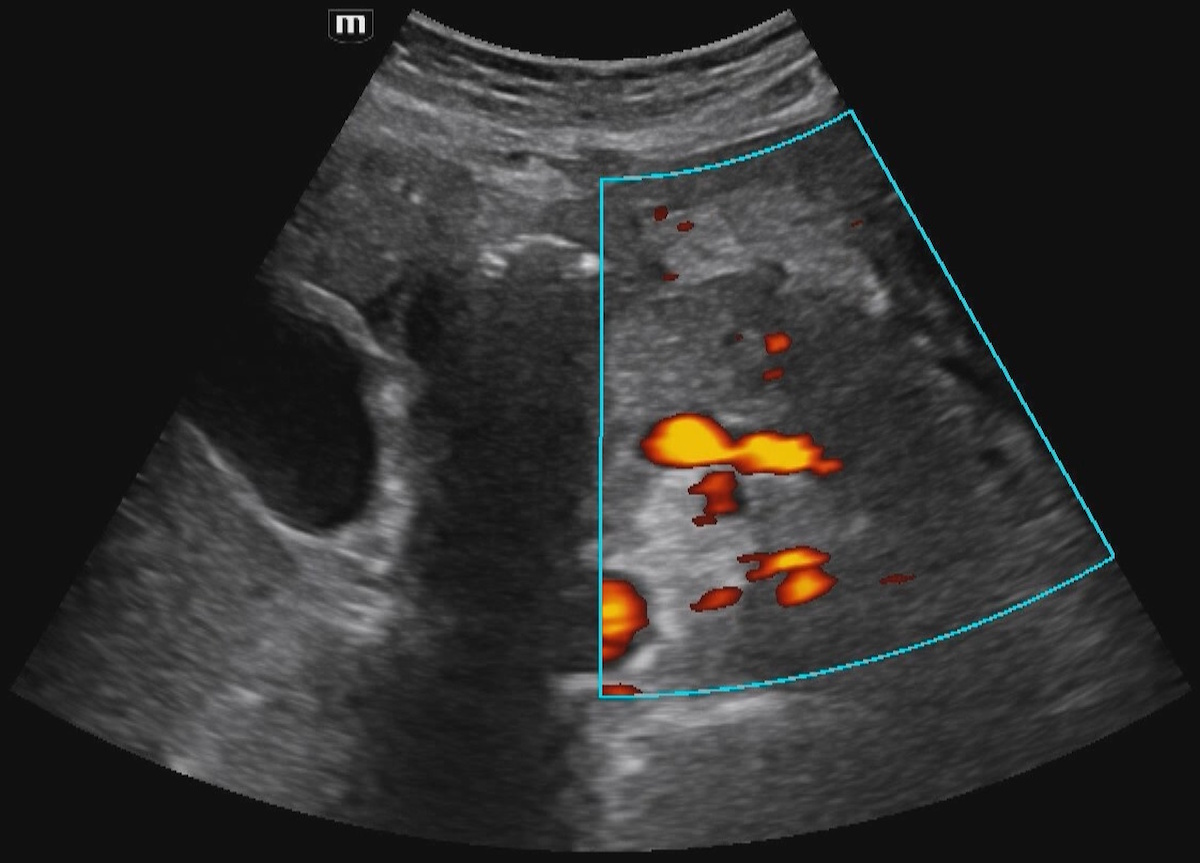
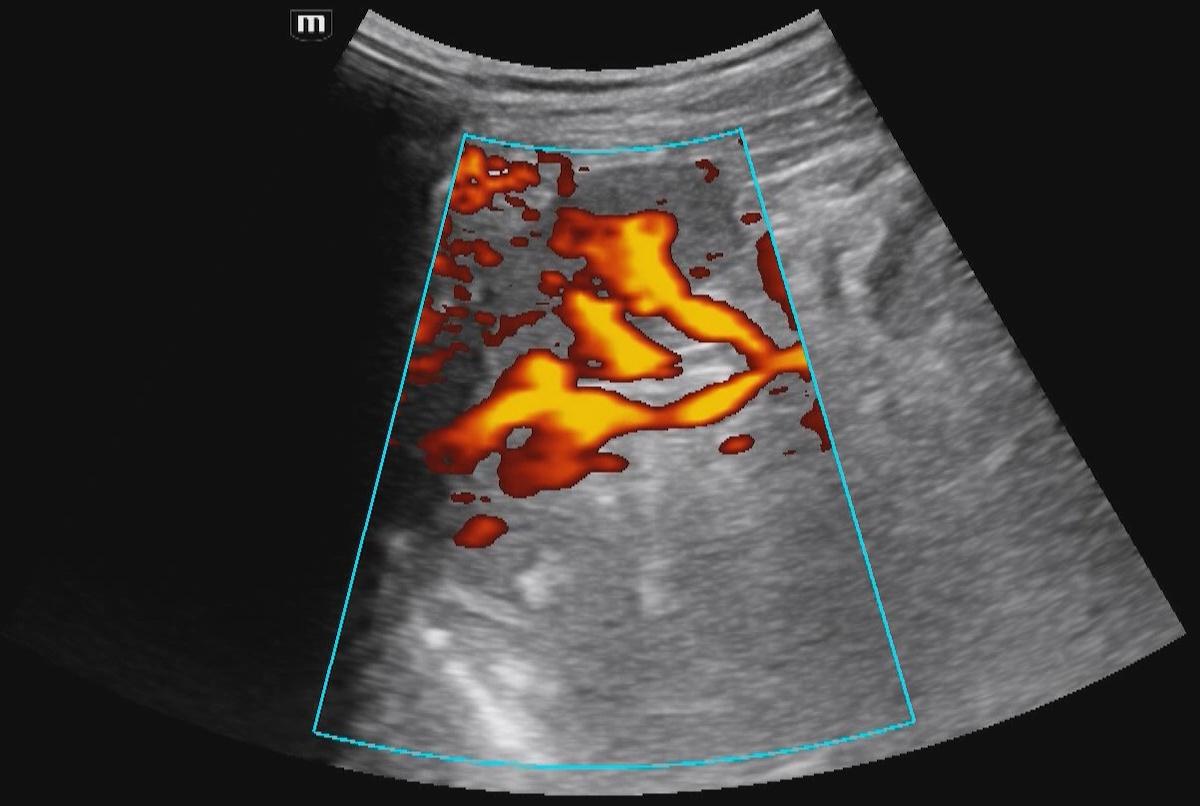
Description of sonographic findings
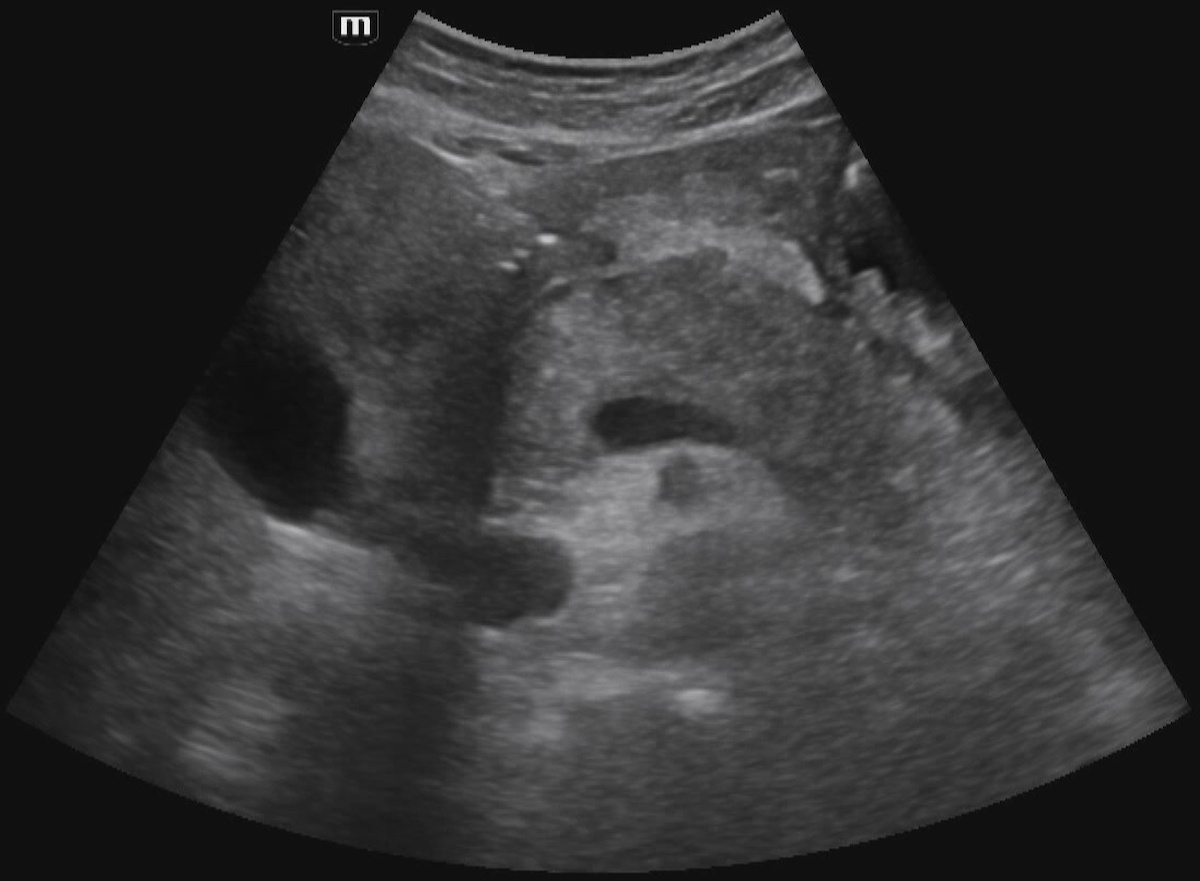
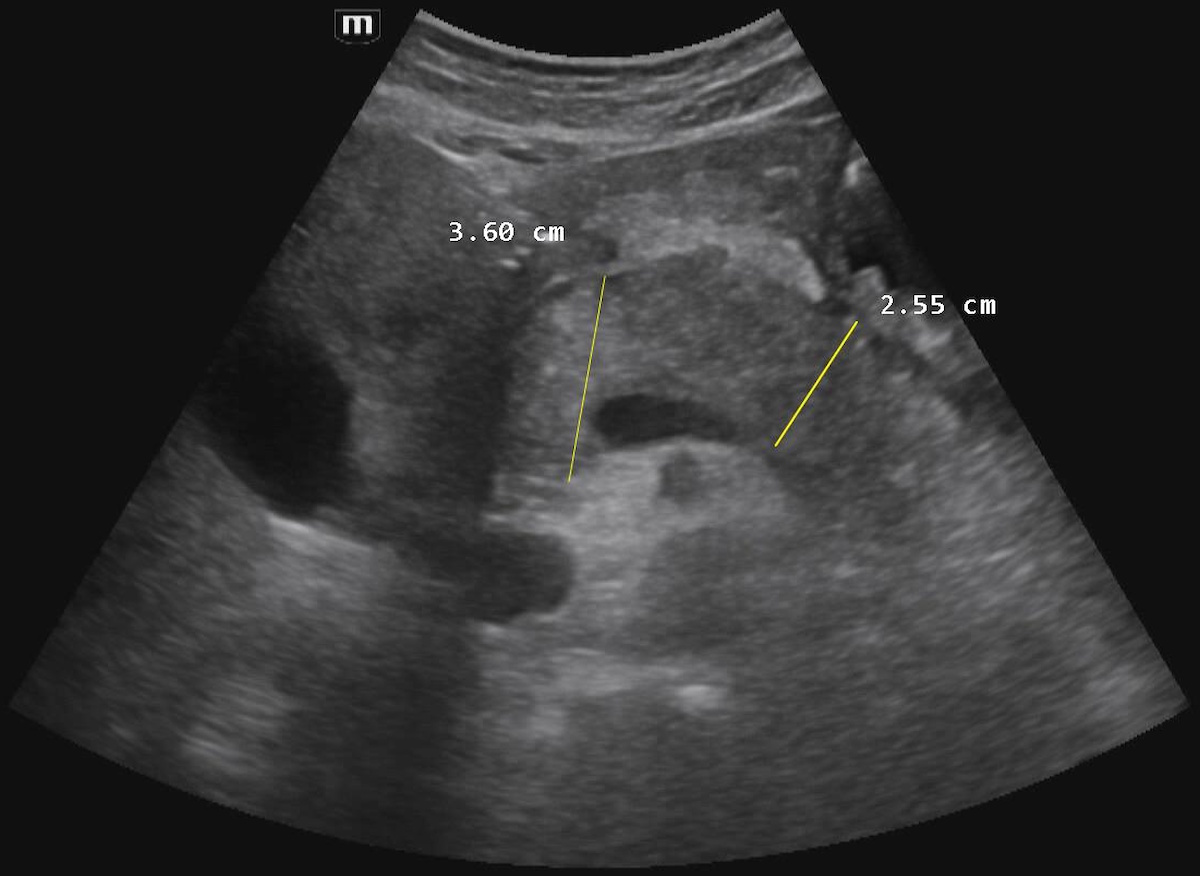
The pancreas is enlarged: the head measures up to 36 mm and the body up to 25 mm; the tail is partially obscured by bowel gas.
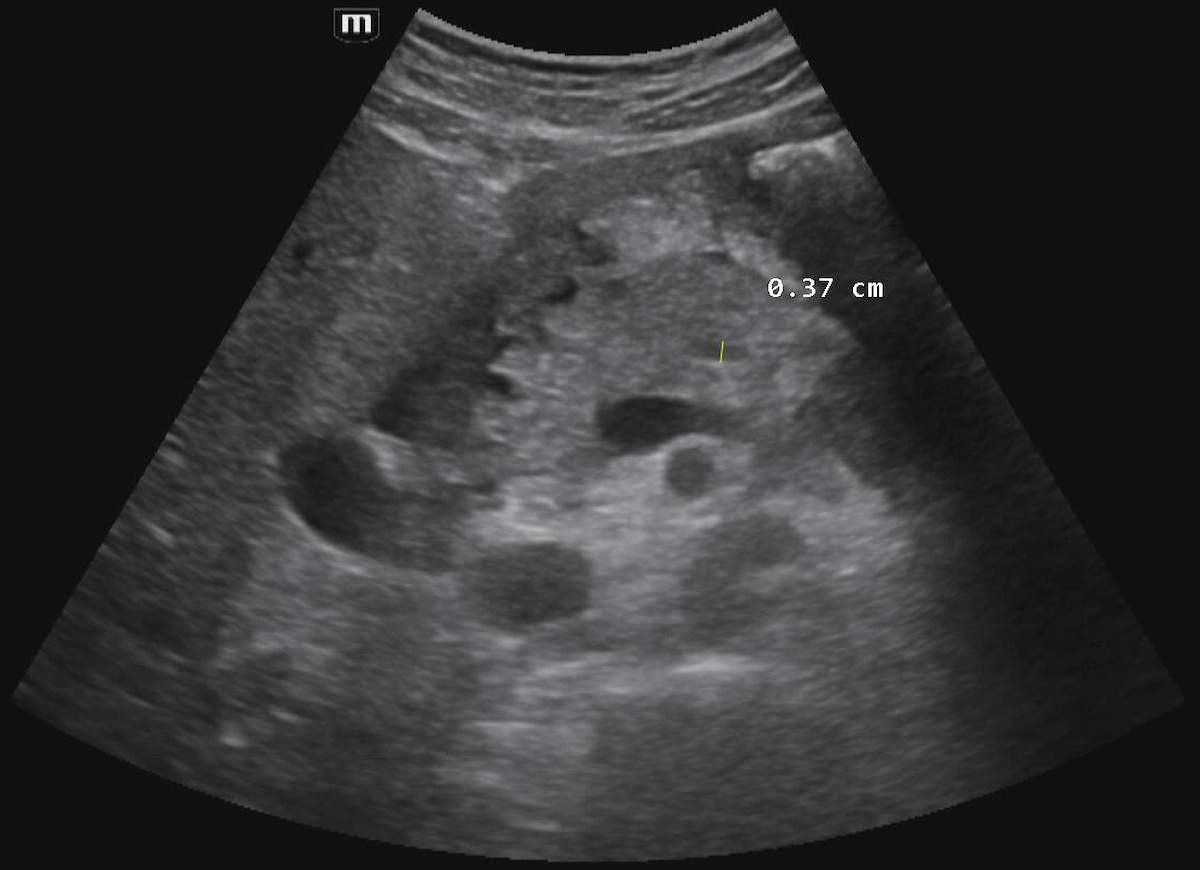
The pancreatic parenchyma is diffusely heterogeneous and predominantly hypoechoic. The pancreatic contours are well defined and focally irregular. No definite focal lesions are identified within the visualized portions of the pancreas. The main pancreatic duct is dilated up to 3.7 mm. Flow within the splenic vein is preserved on Doppler imaging.
Free intraperitoneal fluid is present in the lesser sac along the anterior aspect of the pancreas, measuring up to 7.5 mm in thickness; in the subhepatic space, up to 3.5 mm; in the perisplenic space, up to 5 mm; along the right paracolic gutter, up to 28 mm; and in the pelvis, up to 84 mm.
A thin fluid layer measuring 3–4 mm in thickness is identified in the left retroperitoneum, extending along the anterior renal fascia (Gerota’s fascia).
Conclusion of sonographic findings
Ultrasound findings demonstrate pancreatic enlargement and diffuse inflammatory changes of the pancreatic parenchyma, dilatation of the main pancreatic duct, and free fluid within the peritoneal and retroperitoneal spaces. The overall sonographic findings are consistent with acute pancreatitis.
Final diagnosis
Acute alcoholic pancreatitis
