
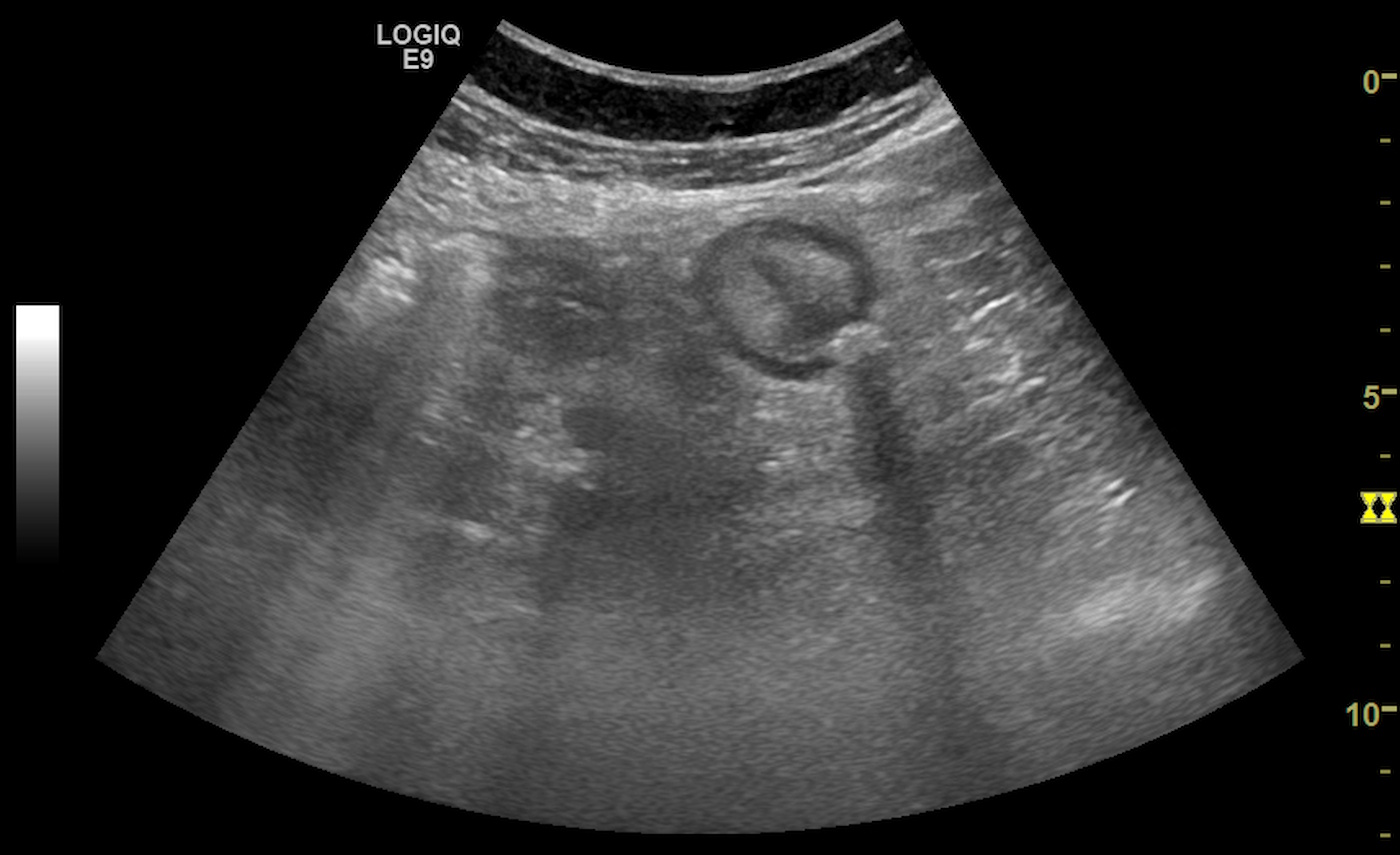
The diagnosis was confirmed by concordant ultrasound and CT findings.
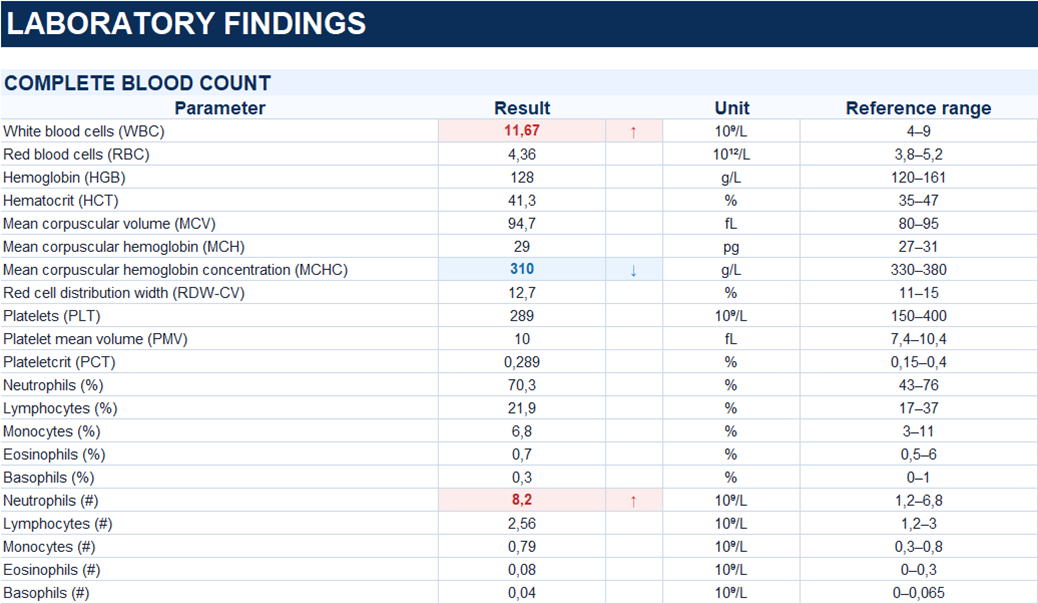
Study method
Ultrasound, CT
Clinical information
A 63-year-old female patient presented with a two-day history of progressively worsening pain in the left lower quadrant. She had taken drotaverine independently without significant improvement.
Due to increasing pain, she sought medical attention and was referred from an outpatient clinic to the hospital emergency department.
The patient denied nausea, vomiting, bowel habit changes, and catarrhal symptoms.
Description of sonographic findings
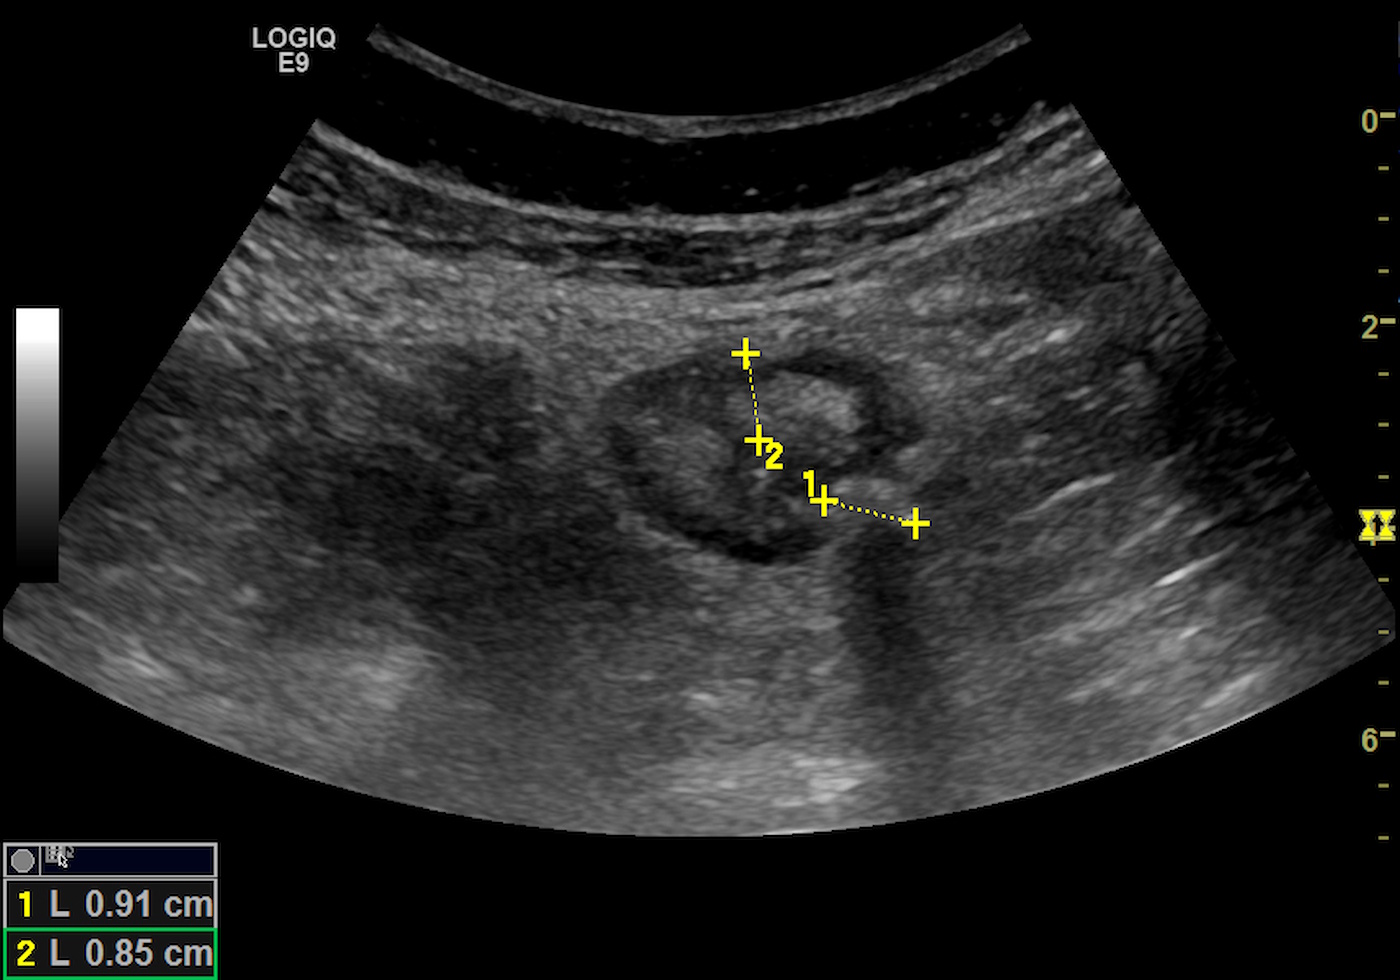
In the region of the descending colon and sigmoid colon, a 9 mm diverticulum is visualized, containing hyperechoic component with posterior acoustic shadowing is identified, likely due to gas and/or dense fecal material.
The adjacent bowel segment demonstrates circumferential wall thickening up to 8 mm with preserved wall layer differentiation.
Increased echogenicity of the surrounding pericolic fat is observed, corresponding to inflammatory infiltration.
Conclusion of sonographic findings
Ultrasound findings are consistent with acute sigmoid diverticulitis with inflammatory infiltration of the pericolic fat.
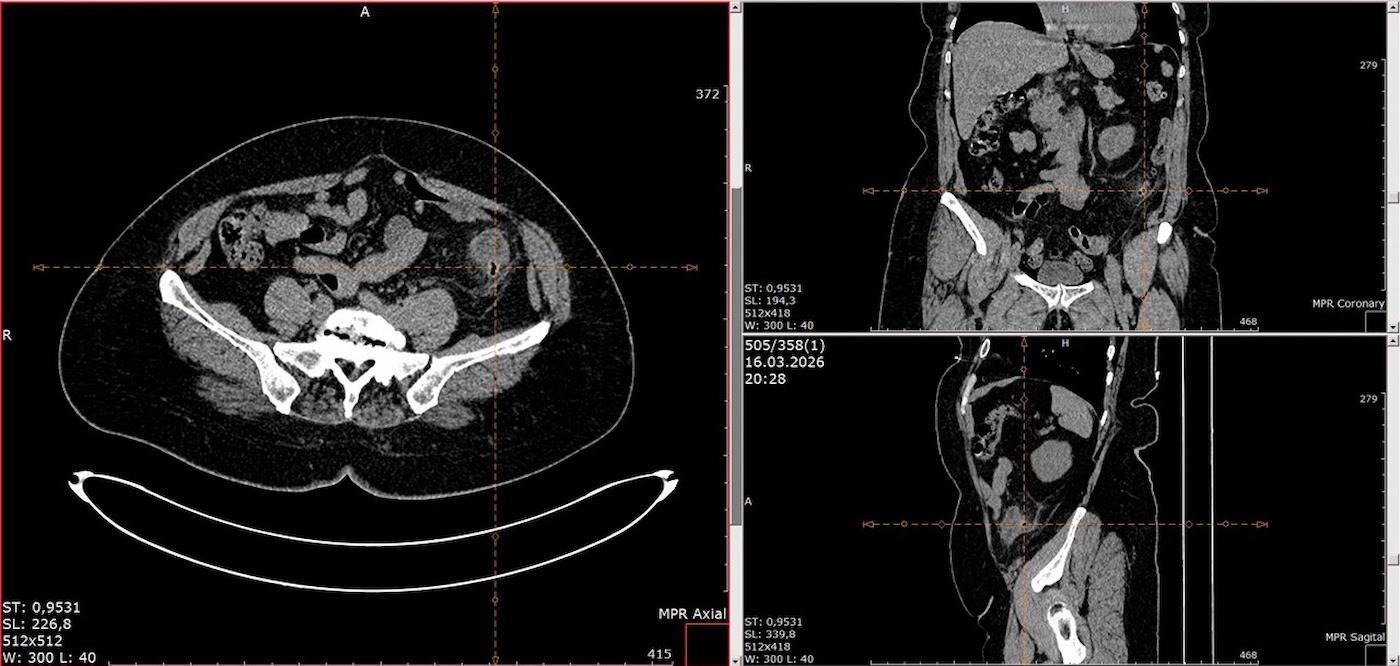
Non-contrast CT
Description of radiographic findings
Circumferential thickening of the sigmoid colon wall up to 13 mm with multiple diverticula measuring up to 9 mm.
Inflammatory infiltration of the pericolic fat is present.
No signs of perforation, abscess formation, or free intraperitoneal gas are identified.
Conclusion of radiographic findings
CT findings are consistent with acute sigmoid diverticulitis.
Final diagnosis
Colonic diverticular disease.
Acute sigmoid diverticulitis (Hinchey Ia) without signs of perforation or abscess formation.
Pitfall
The ultrasound appearance of diverticulitis may be misinterpreted as sigmoid colon malignancy, appendicitis (in cases of a long sigmoid colon), inflammatory bowel disease, or an infiltrative pelvic process.
Key points to consider:
-visualization of the inflamed diverticulum;
-focal tenderness during probe compression;
-inflammatory changes in the pericolic fat;
-preservation of the layered structure of the bowel wall;
-absence of a solid mass lesion.
